How to define the Anion Gap?
The anion gap is a value calculated from a standard blood test that enables clinicians check the level of electrolytes in the body. It is taken from a routine serum chemistry or electrolyte panel and is used to support assessment of acid-base balance. Although the term sounds highly specialized, the idea is straightforward: the result estimates the difference between measured positively charged ions and measured negatively charged ions in the blood.
This difference matters because it can reveal the presence of unmeasured anions or unmeasured cations that are not obvious from a basic panel alone. In clinical practice, the anion gap serves as a diagnostic tool and a quick way to guide result analysis when an acid-base disorder or other metabolic disturbance is suspected.
An anion gap calculator makes this process more convenient by using common lab values to derive the result in seconds. But the number only becomes useful when you know what it means in medical context. A normal result may be comforting, while an abnormal one can point toward issues such as metabolic acidosis, low albumin, or other conditions that call for further review.
Anion Gap Equation and Equation
The usual anion gap equation uses recorded values from the blood, specifically serum sodium, serum chloride, and serum bicarbonate. The standard anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain clinicians use a modified form that includes potassium, but today’s calculators use the shorter version above because it is broadly accepted and handy for routine interpretation.
Here is the core logic behind the equation:
- Sodium represents the main measured cation. Chloride and bicarbonate represent the primary measured anions. The gap indicates the gap between measured positive and negative charges.
When you calculate the anion gap, you are not finding a gap in the literal sense. You are determining the amount of charge carried by unmeasured substances in the blood. That is why the anion gap equation is so valuable for identifying an acid-base disorder and for identifying patterns in a serum chemistry result.
A elevated result suggests extra unmeasured acids or other compounds, while a reduced result can suggest a loss of negatively charged proteins or a measurement problem. Because of that, correct use of the anion gap formula depends on the full lab picture, not just one individual number.
How the Anion Gap Calculator Works
An anion gap calculator is intended to simplify the math and reduce manual errors. You provide the input values from the electrolyte panel, and the calculator performs the calculation steps automatically. In most cases, you provide sodium, chloride, and bicarbonate values, then the tool produces the anion gap along with a reference range or interpretation note.
The process usually is as follows:
- Input the sodium value from the blood test. Enter the chloride value. Provide the bicarbonate value. Examine the calculated result and match up it with the reference range.
Many users turn to an online calculator because it supports quick pattern recognition during result analysis. It is especially useful when reviewing an electrolyte panel in a busy clinical setting or when trying to understand whether a lab pattern suggests a broader metabolic issue.
Even though the calculator is simple, the numbers still need context. A value that falls within the reference range may still be abnormal if albumin is low or if another condition is changing the baseline. That is why the calculator is best viewed as a first step in interpretation, not the final answer.
In practical use, the calculator helps identify whether the result fits a typical normal anion gap pattern or whether further review is needed. It can also support decision-making when the goal is to understand possible causes of metabolic acidosis or other acid-base changes.
Expected Anion Gap Range and What Influences It
The reference range for the anion gap differs slightly by laboratory because of differences in measurement methods, analyzer calibration, and reporting practices. Here lab variation matters. A result that is considered normal in one setting may be slightly different in another, so the lab’s own reference range should take priority.
Multiple factors can alter the number:
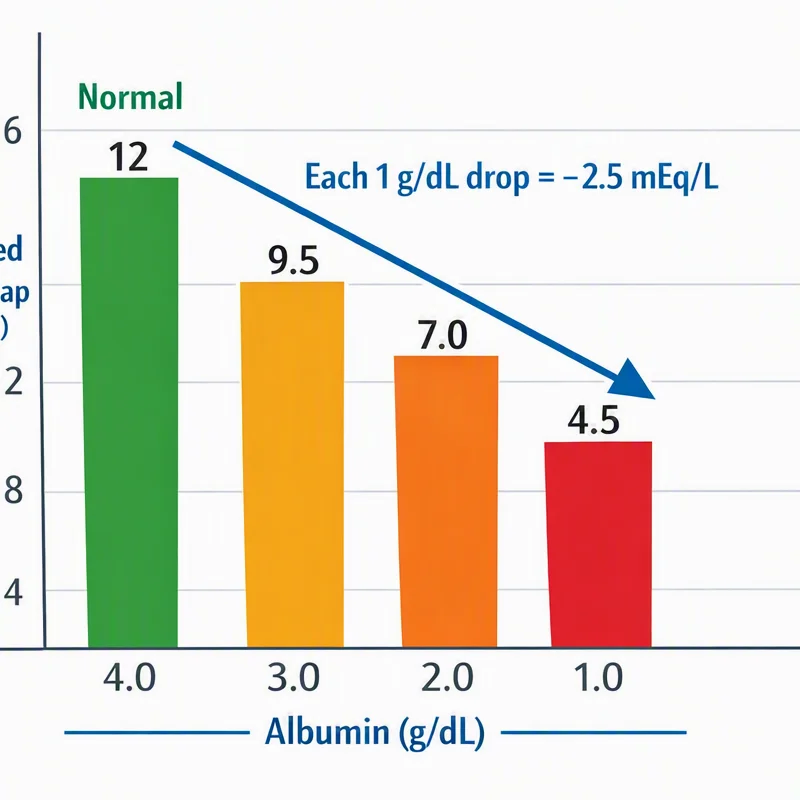
- Albumin: Because albumin is a primary unmeasured anion, lower levels can lower the measured gap. Lactate: Elevated lactate can increase the gap because it adds unmeasured anions. Lab variation: Different instruments and methods may yield slightly different values.
Albumin is especially significant because it is one of the main contributors to the anion gap. When albumin is low, the normal anion gap may appear artificially reassuring. In those cases, an albumin correction or albumin adjustment may be needed to calculate a more accurate corrected anion gap.
This matters because a patient can have a meaningful acid-base problem even if the raw number seems normal. Therefore, interpreting the value without checking albumin can lead to overlooked findings. Similarly, increased lactate can shift the result upward even before other abnormalities are obvious.
Raised Anion Gap: Frequent Causes
A elevated anion gap usually points to the presence of unaccounted-for acids in the blood. The main clinical concern is acid-base disturbance, where acid accumulates or bicarbonate is consumed in a way that elevates the calculated gap.
These causes include:
- Lactic acidosis, often related to impaired tissue oxygen delivery, severe illness, or decreased lactate clearance. Ketone-related acidosis, which can occur when ketone bodies rise during insulin deficiency, starvation, or other metabolic stress. Renal failure, where reduced acid excretion allows acids to build up. Toxin exposure, including certain substances that generate unmeasured acids or interfere with normal metabolism.
These causes are important because they indicate different treatment pathways. For example, lactic acid buildup suggests a search for tissue hypoperfusion or severe infection, while ketoacidosis points toward abnormal fat metabolism and requires a different management approach. Renal failure may result in acid retention over time, and toxin exposure can produce a dangerous metabolic picture that needs urgent assessment.
A high value is not a diagnosis by itself. It is a clue that should be read alongside symptoms, history, and the rest of the blood test results. In many cases, it prompts additional testing to identify the underlying cause and to determine how severe the metabolic disturbance is.
Decreased Anion Gap: Typical Causes
A reduced anion gap is less common than a high one, but it can still be clinically meaningful. One of the most common explanations is hypoalbuminemia, because albumin is a negatively charged protein that contributes to the normal gap. When albumin falls, the calculated value can fall with it.
Additional common causes include:
- Paraproteinemia, where abnormal proteins in the blood alter the balance of measured and unmeasured ions. Lab error, including specimen issues or measurement problems that distort the reported electrolytes.
Hypoalbuminemia is especially important because it can obscure a serious condition if the result is interpreted without an albumin correction. In some patients, the corrected value may reveal a more significant disorder than the unadjusted number suggests. This is why a corrected anion gap can be more useful than the raw calculation alone.
Paraproteinemia should be considered when abnormal proteins are present, particularly if other findings do not match the apparent result. And because lab error is always possible, an unexpected low result should be reviewed carefully before drawing conclusions. Repeating the test or checking the full electrolyte panel may help confirm whether the number is real.
Clinical Use of the Anion Gap in Acid-Base Disorders
The anion gap is most valuable when used as part of a broader assessment of acid-base disorders. It helps distinguish different types of metabolic acidosis and strengthens the work of pattern recognition when reviewing a blood test, electrolyte panel, and serum chemistry https://blogfreely.net/budolfwboy/how-to-use-an-anion-gap-calculator-in-blood-chemistry-results results in combination.
In practice, the anion gap helps clarify questions such as:
- Is the acidosis related to accumulation of unmeasured acids? Might the pattern suggest bicarbonate loss instead? Is the gap elevated enough to warrant looking for lactate, ketones, toxins, or renal dysfunction?
Another important concept is the delta gap, which contrasts the change in anion gap with the change in bicarbonate. This can help reveal mixed disorders, where more than one metabolic process is happening at the same time. That is useful because a patient may have a high anion gap acidosis and another acid-base problem concurrently.
A blood gas is often interpreted alongside the anion gap to give a fuller picture of acid-base status. The blood gas shows pH and respiratory compensation, while the anion gap helps reveal the underlying metabolic component. Together, they improve clinical significance and help with cause assessment.
This is why the anion gap remains a practical diagnostic tool: it turns a simple lab calculation into a practical guide for evaluating complex metabolic disturbances.
Interpreting Results Carefully
Good clinical interpretation needs more than just checking a single value. The anion gap should be reviewed in the light of signs, the entire electrolyte panel, medication history, kidney function, and any additional signs of illness. A result that appears abnormal may be explained by timing, fluid status, protein changes, or measurement differences.
Careful interpretation involves several steps:
- Confirm the values used in the calculation. See whether the lab’s reference range changes from other sources. Review albumin and consider albumin adjustment if needed. Check for signs of electrolyte imbalance or metabolic acidosis. Find clinical clues that back up or reduce a suspected cause.
If the result suggests a serious issue, a medical evaluation is essential. This is especially true when symptoms such as confusion, rapid breathing, dehydration, vomiting, or severe weakness are present. The anion gap is useful, but it does not replace a full assessment of the person and the illness.
In simple terms, the number should inform the next step, not serve as the final conclusion. Pairing the calculator result with clinical context improves accuracy and reduces the risk of missing an important problem.
FAQ
What is the anion gap calculator used for?
The anion gap calculator is used to calculate the anion gap from common blood test values, usually sodium, chloride, and bicarbonate. It helps with interpretation of acid-base balance and can point toward a metabolic disturbance such as metabolic acidosis.
What is the formula for calculating the anion gap?
The most common anion gap equation is: sodium minus the sum of chloride and bicarbonate. In short, the anion gap formula is sodium − (chloride + bicarbonate). Some versions may include potassium, but the simpler formula is widely used.
What’s a normal anion gap result?
The normal range depends on the laboratory and analysis used, so the listed range on the lab report should be checked initially. A result in the normal range generally suggests no major build-up of hidden acids, but low albumin and measurement differences can influence the number.
What leads to a high anion gap?
A increased anion gap is often caused by metabolic acidosis from issues like excess lactic acid, ketosis-related acidosis, impaired kidney function, or poisoning. These issues introduce unmeasured acids to the blood and elevate the calculated number.
Can a low anion gap suggest a medical problem?
Yes. A decreased anion gap can be associated with low albumin, protein abnormalities, or lab error. It may also show other changes in electrolytes or proteins, so it should be evaluated in context rather than overlooked.