How the Anion Gap Measures in Suspected Poisoning
The anion gap is a useful diagnostic marker in the evaluation of pH balance, especially when a toxic ingestion is considered. It helps clinicians spot unclear metabolic acidosis by reviewing the key measured electrolytes in a routine electrolyte panel. Practically, the anion gap is one of the fastest ways to see that something abnormal is happening in the blood chemistry before a full toxicology picture is available.
During emergency care, a widened anion gap can suggest a metabolic derangement caused by acid accumulation, impaired clearance, or exposure to a toxin. This is especially important in suspected toxic alcohols, where early recognition can guide urgent treatment. An Anion Gap Calculator helps streamline lab interpretation by organizing the key values that support clinical assessment.
The anion gap is not a diagnosis by itself. It is a signal that must be interpreted alongside the patient’s symptoms, history, serum chemistry, and related tests such as serum osmolality, arterial blood gas, and other markers of organ stress. In suspected poisoning, it is best thought of as one piece of a larger diagnostic puzzle rather than a standalone answer.
How Ethylene Glycol Poisoning Changes Lab Results
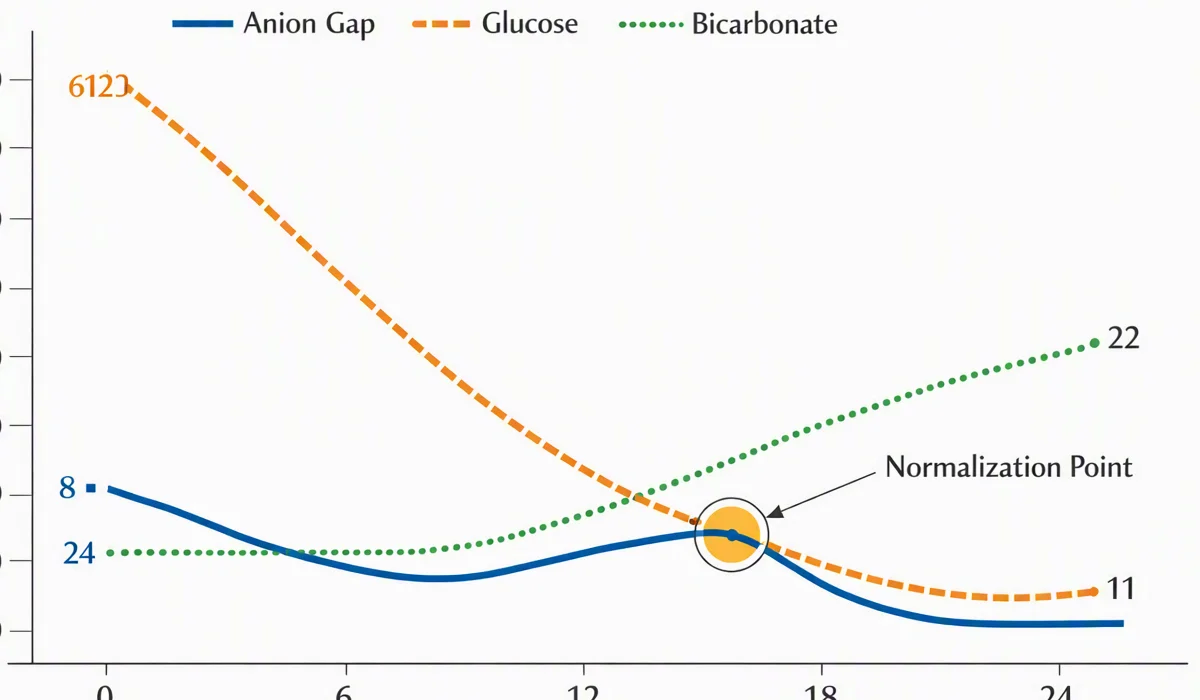
Ethylene glycol exposure is a well-known cause of ethylene glycol poisoning and can cause a serious sequence of laboratory findings. Soon after ingestion, the key clue may be an elevated osmolar gap, indicating the presence of unchanged parent compound in the blood. As metabolism advances, the parent alcohol is converted into glycolic acid and other acidic metabolites, which drive high anion gap changes and worsening metabolic acidosis.
This shift over time is a major reason why toxic alcohol ingestion can be missed. A patient may present with only subtle symptoms initially, while the labs later progress into a profound high anion gap metabolic acidosis. That is why timing of ingestion matters so much in laboratory interpretation. Early on, the osmolality profile may be more informative; afterward, the anion gap may become the more useful clue.
Ethylene glycol poisoning also damages the kidneys and nervous system. Renal injury can arise as toxic metabolites and calcium oxalate deposition damage renal tissue. Neurologic symptoms may include confusion, incoordination, or declining mental status. In severe cases, patients may also experience visual disturbances, though this feature is more classically associated with methanol. Still, the overall picture of toxic alcohol exposure requires careful clinical assessment because presentations often resemble each other.
Urine microscopy may reveal calcium oxalate crystals, which are supportive of ethylene glycol exposure when seen in the right context. However, these crystals are not required for diagnosis and should never delay treatment when suspicion is high. The overall pattern—osmolar gap initially, anion gap subsequently, worsening acid-base status, and organ injury—often provides the clearest clue.
How to Use the Anion Gap Calculator
A Anion Gap Calculator relies on common serum values to assess whether unmeasured acids are present. The calculation is based on the major cations and anions in the blood and is often used to a serum bicarbonate-centered review.
The standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
To use it, enter the patient’s sodium, chloride, and bicarbonate values from the serum chemistry panel. A few formulas include potassium, but the standard clinical form excludes it. A low bicarbonate value, when paired with an increased gap, often supports the presence of metabolic acidosis due to unmeasured acids.
For instance, if sodium is 140, chloride is 100, and bicarbonate is 10, the anion gap is 30. That pattern points to a substantial accumulation of acids and should prompt immediate evaluation for underlying causes such as toxic alcohol ingestion, lactic acidosis, diabetic ketoacidosis, or renal failure.
In suspected poisoning, the calculator should be paired with related data points from the electrolyte panel and emergency evaluation. The anion gap https://anion-gap-estimator585.inkharbory.com/posts/how-to-operate-an-anion-gap-calculator-for-high-chloride-acidosis is not isolated from the rest of the chemistry profile; it is most informative when viewed together with measured osmolality, calculated osmolality, and the overall acid-base balance.
Meaning: Typical, Elevated, and Critical Results
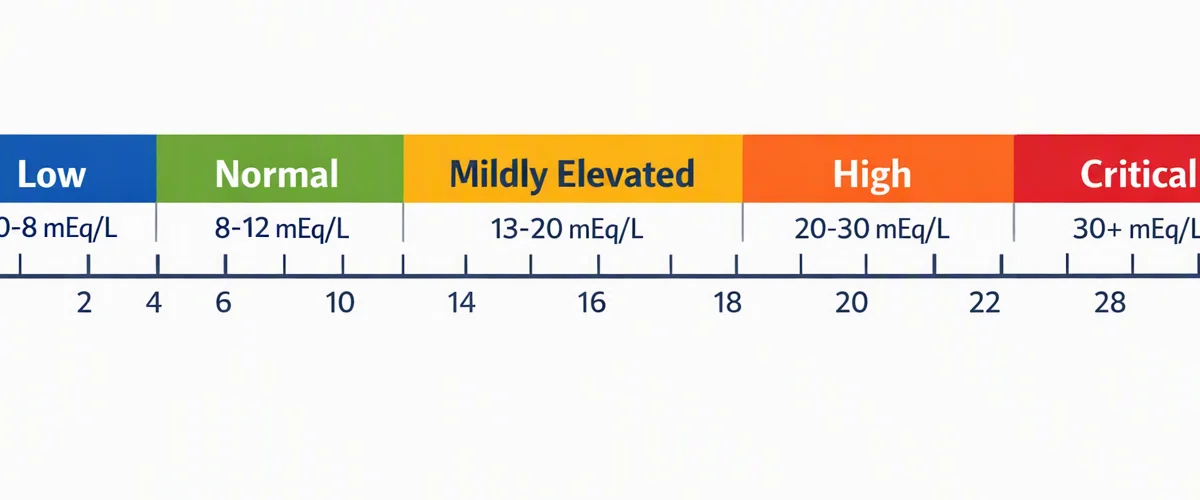
Interpreting the usual range for the anion gap is important before reaching conclusions. Different laboratories may use different reference intervals, but a standard normal result suggests that there is no major buildup of unlisted acids. A normal value, however, does not always exclude poisoning, especially if the patient presents early after ingestion.
An elevated result indicates that acidic byproducts are accumulating, which is often seen in anion gap metabolic acidosis with a high gap. In suspected ethylene glycol poisoning, this is a concerning signal because glycolic acid and related metabolites can markedly increase the gap. The degree of elevation, combined with symptoms and other testing, helps determine urgency.
Clinical assessment should always include the broader acid-base disorder. A patient may have respiratory compensation, mixed disorders, or coexisting processes that blur the interpretation. An arterial blood gas can help confirm the severity of acidemia and show whether the body is attempting to compensate. At the same time, a serum chemistry panel gives the numerical support needed to identify the gap itself.
A critical result is one that fits with significant poisoning, severe acidosis, or worsening organ dysfunction. In that setting, waiting for confirmatory testing may be unsafe. The calculator can support decision-making, but it should not replace urgent bedside judgment, especially when the clinical picture is strongly suggestive of toxic alcohol exposure.
Primary Differential Diagnoses and Interferences
Multiple disorders can resemble ethylene glycol poisoning and must be reviewed during medical evaluation. One important differential is methanol poisoning, a further toxic alcohol ingestion that can also cause high anion gap metabolic acidosis and an osmolar gap early in the course. Methanol more commonly causes prominent visual symptoms, but overlap is frequent enough that both require prompt evaluation.
Diabetic ketoacidosis is another key confounder. It can result in a markedly elevated anion gap from ketone accumulation, along with dehydration, nausea, and altered mental status. In a patient with diabetes, this may be a more likely explanation, but it should not automatically rule out toxic alcohol exposure if the history is unclear.
Lactic acidosis can also elevate the anion gap. Sepsis, hypoperfusion, seizures, or severe hypoxia may all lead to lactate accumulation and a similar metabolic picture. In these cases, the underlying cause is usually apparent from the broader clinical scenario, but the lab pattern can still resemble toxic ingestion.
Renal failure is a further key confounder because reduced acid clearance can create metabolic acidosis. Uremia may elevate the gap and complicate interpretation, especially if the patient already has abnormal baseline kidney function. This is why lab interpretation should always account for the full history, kidney status, and current illness severity.
Other possibilities include mixed acid-base states, ketoacidosis from other causes, and laboratory error. Because multiple disorders can coexist, a single abnormal value should not end the evaluation. The most reliable approach is to integrate the calculator result with toxicology consultation, bedside findings, and confirmatory studies.
When to Escalate: Emergency Evaluation and Treatment
Suspected ethylene glycol poisoning is a serious emergency. If the pattern suggests toxic alcohol exposure, immediate escalation is recommended, especially when there is increasing acidosis, altered mental status, or evidence of kidney injury. Prompt involvement of toxicology and poison control can help direct the next steps quickly.
Fomepizole is a key antidotal therapy because it blocks alcohol dehydrogenase and reduces the conversion of ethylene glycol into harmful metabolites. This can limit the buildup of glycolic acid and reduce further metabolic damage. In many cases, treatment is started before confirmatory levels return if the clinical suspicion is substantial.
Hemodialysis may be necessary for severe poisoning, significant metabolic acidosis, very high toxic alcohol burden, renal injury, or clinical deterioration. Dialysis helps clear the parent compound and metabolites while restoring acid-base abnormalities. It becomes especially vital when the patient is critically ill or not improving with initial management.
Supportive care in emergency medicine may include airway protection, fluid resuscitation, correction of severe acidemia, and close monitoring of electrolytes and renal function. An arterial blood gas, serum chemistry, and serial serum osmolality measurements can help follow response. The goal is to treat without delay, because delays can lead to worsening organ injury and more severe outcomes.
Restrictions of the Calculator in Potential Poisoning
The Anion Gap Calculator is valuable, but it has significant constraints in real-world use. One major limitation is the time of ingestion. Early after exposure, the anion gap may still be normal because the toxic metabolites have not yet accumulated. Later, the osmolar gap may fall as the parent alcohol is metabolized, even as the acidosis worsens.
Lab limitations also matter. Changes in assay methods, specimen handling, and reference intervals can affect results. In some cases, the patient’s true acid-base status may be more complex than the calculator suggests. An isolated number cannot show the full effect of mixed disorders or rapidly changing physiology.
A notably important concern is the false normal anion gap. This can occur early in poisoning, after treatment has begun, or when other electrolyte changes mask the widening gap. A normal calculator result therefore does not safely dismiss ethylene glycol poisoning if the history, symptoms, or osmolality data are still concerning.
For these reasons, clinical judgment remains vital. The calculator should support, not replace, bedside reasoning. If the patient has poisoning symptoms, unexplained acidosis, or a suspicious ingestion history, treatment and toxicology consultation should proceed even if the gap is not clearly elevated yet.
FAQ
What does an elevated anion gap suggest in ethylene glycol poisoning?
An elevated anion gap usually means that acidic substances not directly measured are gathering in the blood. In ethylene glycol poisoning, this commonly reflects accumulation of glycolic acid and related acidic metabolites, which produce high anion gap metabolic acidosis. The result backs up the diagnosis but should be interpreted with the rest of the clinical assessment and toxicology data.
Can ethylene glycol poisoning have a normal anion gap?
Yes, it can. The anion gap can be normal early after ingestion, before toxic metabolites accumulate. It may also appear normal after partial treatment or if other factors alter the lab pattern. That is why a normal result does not rule out poisoning when the history, symptoms, or osmolality findings are concerning.
How does the osmolar gap compare with the anion gap?
The osmolar gap compares measured osmolality with calculated osmolality and helps detect unmeasured dissolved substances in the blood, especially early after toxic alcohol ingestion. The anion gap reflects unmeasured charged particles, usually acidic metabolites, and often becomes more prominent later. In ethylene glycol poisoning, the osmolar gap may be higher first, followed by a rising anion gap as metabolism continues.
At what point should fomepizole or hemodialysis be considered?
Fomepizole should be considered when ethylene glycol poisoning is suspected strongly enough that waiting could be dangerous. Hemodialysis is considered when there is severe acidosis, significant renal injury, high toxic alcohol burden, or clinical deterioration. Both decisions are often made with toxicology input and based on the overall picture rather than a single lab value.
Which other disorders can mimic ethylene glycol poisoning?
Important mimics include methanol poisoning, diabetic ketoacidosis, lactic acidosis, and renal failure. Each can produce metabolic acidosis and abnormal lab patterns that resemble toxic alcohol ingestion. Careful lab interpretation, arterial blood gas review, serum osmolality assessment, and clinical history help distinguish these conditions.
In presumed ethylene glycol poisoning, the Anion Gap Calculator is often most useful when it is used as part of a wider diagnostic workflow. The best approach combines the calculator, serum osmolality, arterial blood gas, electrolyte panel findings, and the patient’s evolving symptoms. This combined approach improves the chance of recognizing toxic alcohol ingestion early and initiating appropriate emergency treatment before irreversible harm occurs.